Erfolgreich durch internationale Zusammenarbeit
Hepatology and Transplantation
Cite as: Archiv EuroMedica. 2026. 16; 4. DOI 10.35630/2026/16/Iss.4.07
Received 16 June 2026;
Accepted 28 July 2026;
Published 6 August 2026
PROGRESSIVE MULTIFOCAL LEUKOENCEPHALOPATHY AFTER ORTHOTOPIC LIVER TRANSPLANTATION: A SYSTEMATIC REVIEW
Kamil Andruszkiewicz1 
 ,
Julia Bąk1 ,
Bogna Błachowska2 ,
Wojciech Frączyk1 ,
Natalia Jasińska3 ,
Mateusz Krysiak1 ,
Bartosz Machnio4 ,
Katarzyna Mania1 ,
Agnieszka Stankowska1 ,
Agata Świątek5 ,
Natalia Turzyńska1
1 University Clinical Centre in Gdansk, Poland
2 St. Vincent de Paul Hospital, Gdynia, Poland
3 7th Naval Hospital, Gdansk, Poland
4 Medical University of Warsaw, Poland
5 St. Adalbert Hospital, Gdansk, Poland
 download article (pdf)
ABSTRACT
Background
Progressive multifocal leukoencephalopathy is a demyelinating disease of the nervous system. It is caused by reactivation of the John Cunningham Virus in patients with compromised immune systems. It is well described in other diseases, but occurrence after orthotopic liver transplantation is not well documented.
Aims
The aim of this systematic review is to summarise data about neurological presentation, immunosuppressive treatment, diagnosis, treatment and outcomes in patients with progressive multifocal leukoencephalopathy after orthotopic liver transplantation.
Materials and Methods
PubMed and Scopus were searched on 6 April 2026 without date restrictions. Case reports, case series, and observational studies providing individual patient data on progressive multifocal leukoencephalopathy after orthotopic liver transplantation were included. Studies without liver transplant recipients or without original patient data were excluded. The reference lists of the included publications were also screened for additional eligible studies.
Results
Sixteen studies reporting a total of 17 patients were included. The interval between liver transplantation and diagnosis of progressive multifocal leukoencephalopathy ranged from 1.5 to 204 months, with a median of approximately 10 months among the 14 patients with available data. Clinical manifestations were heterogeneous and most commonly included motor deficits, cognitive impairment, coordination or gait disturbances, and visual symptoms. Diagnosis was based mainly on brain magnetic resonance imaging and detection of John Cunningham virus DNA in cerebrospinal fluid. Reduction or discontinuation of immunosuppression was the most frequently reported therapeutic approach. Twelve of the 17 patients died.
Conclusions
Progressive multifocal leukoencephalopathy after orthotopic liver transplantation is a rare but severe complication associated with high mortality. It may develop within the first months or many years after transplantation. The available evidence is insufficient to determine the optimal strategy for reducing immunosuppression, particularly because of the risk of graft rejection.
Keywords: Immunosuppression; Opportunistic Infections; Central Nervous System Diseases; Risk Factors; Cerebrospinal Fluid
INTRODUCTION
Progressive multifocal leukoencephalopathy is an opportunistic infection of the central nervous system caused by reactivation of the John Cunningham virus (JCV) [1,2]. Primary John Cunningham virus (JCV) infection is usually asymptomatic, and serological evidence of previous exposure is found in approximately 50% to 80% of adults, with seroprevalence increasing with age [3,4,5]. In immunocompromised patients, viral reactivation may result in infection of oligodendrocytes, progressive demyelination, and neurological deterioration [6].
Historically, PML was most frequently associated with advanced HIV infection. It has also been reported in patients with hematological malignancies, individuals receiving monoclonal antibody therapy, and solid organ transplant recipients [1,7,8,9]. Earlier reports attributed approximately 80% of PML cases to HIV infection, whereas more recent data suggest that HIV accounts for about 50% of cases. Hematological malignancies account for approximately 10%, while another 10% are associated with sarcoidosis, primary immunodeficiency syndromes, rheumatological diseases, and transplantation. Therapies used for multiple sclerosis, including natalizumab, have been associated with less than 5% of reported PML cases [7,10,11].
PML after orthotopic liver transplantation is rare but clinically important. It may develop within the first months after transplantation or many years later, and its initial manifestations are often nonspecific. Reported symptoms include cognitive impairment, motor deficits, speech disturbances, visual abnormalities, ataxia, and seizures. The disease may progress rapidly and result in severe neurological disability or death [12–27].
Management is particularly difficult in liver transplant recipients. Reduction or withdrawal of immunosuppressive therapy may allow recovery of antiviral immune responses, but it may also increase the risk of graft rejection. Immune recovery may additionally be complicated by immune reconstitution inflammatory syndrome [12,28,29,30]. No established antiviral treatment for JCV is currently available, and published therapeutic experience is limited.
Available evidence on PML after orthotopic liver transplantation remains fragmented and is derived mainly from individual case reports and small case series [12–27]. The reported cases differ considerably in the interval between transplantation and PML diagnosis, immunosuppressive treatment, clinical presentation, diagnostic methods, therapeutic management, duration of follow-up, and outcome. Consequently, it remains unclear whether specific clinical patterns can be identified, whether particular immunosuppressive regimens are associated with PML development, and how immunosuppression should be modified after diagnosis while minimizing the risk of graft rejection. A structured synthesis of the available data is therefore needed.
AIM
The aim of this systematic review is to summarize published evidence on progressive multifocal leukoencephalopathy after orthotopic liver transplantation.
The objectives are:
- To describe the clinical characteristics of affected patients and the interval between liver transplantation and PML diagnosis.
- To summarize the immunosuppressive regimens used before PML diagnosis and the subsequent changes in immunosuppressive therapy.
- To systematize neurological manifestations, neuroimaging findings, and methods of diagnostic confirmation.
- To summarize the reported treatment approaches and clinical outcomes.
MATERIALS AND METHODS
This systematic review was conducted in accordance with the PRISMA 2020 guidelines [31]. PubMed and Scopus were searched on 6 April 2026 without date restrictions.
The PubMed search query was: ("progressive multifocal leukoencephalopathy"[Title/Abstract] OR PML[Title/Abstract]) AND ("liver transplantation"[Title/Abstract] OR "liver transplant"[Title/Abstract] OR "Liver Transplantation"[MeSH Terms]).
The Scopus search query was: TITLE-ABS-KEY("progressive multifocal leukoencephalopathy" OR PML) AND TITLE-ABS-KEY("liver transplantation" OR "liver transplant").
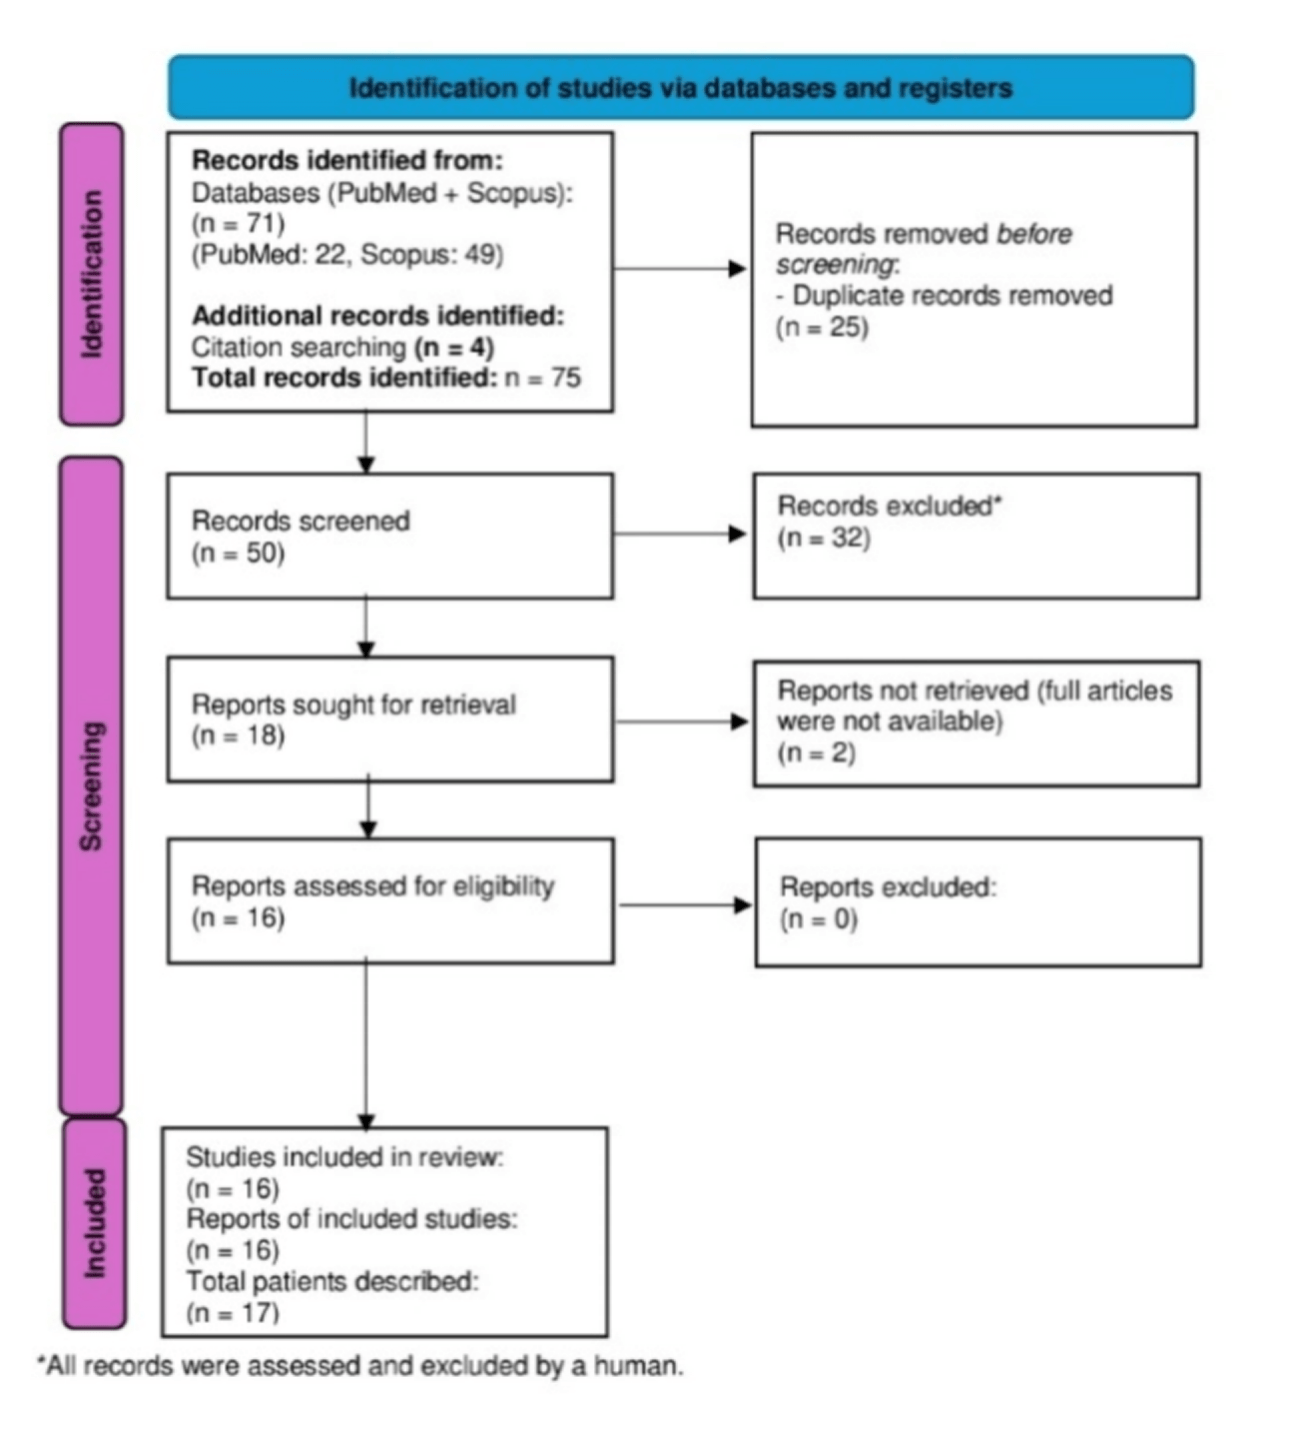
Case reports, case series, and observational studies reporting individual patients with PML after orthotopic liver transplantation were included. Studies involving patients without liver transplantation or publications without original patient data were excluded. The reference lists of the identified publications were also screened for additional eligible studies. Duplicate records were removed before screening. The study selection process is presented in Figure 1.
The extracted variables included age, sex, etiology of liver disease, immunosuppressive treatment before and after PML diagnosis, interval from transplantation to PML diagnosis, neurological manifestations, neuroimaging findings, method of diagnostic confirmation, additional treatment, and outcome.
Because of the small number of cases and the heterogeneity and incompleteness of the reported data, a descriptive qualitative synthesis was performed, and no meta-analysis was conducted. The median interval between liver transplantation and PML diagnosis was calculated for the 14 patients with available data. Early-onset PML was defined as diagnosis within 12 months after transplantation, and late-onset PML as diagnosis more than 12 months after transplantation. Mortality was calculated using all 17 included patients as the denominator. Patients with missing data were excluded only from analyses requiring the unavailable variable.
The methodological quality of the included publications was not assessed.
Figure 1. PRISMA 2020 flow diagram of the study selection process [31].
RESULTS
From 75 identified records, 16 studies comprising 17 patients were included after screening and eligibility assessment. Fifteen studies reported one patient each, and one study reported two patients. All included publications were case reports or small case series. The patients were adults and included 10 women and 7 men. The interval between orthotopic liver transplantation and PML diagnosis ranged from 1.5 to 204 months.
All patients were on immunosuppressive therapies, which included: calcineurin inhibitors (tacrolimus, cyclosporine), corticosteroids and antimetabolites (mycophenolate mofetil). Combination therapy (calcineurin inhibitors + antimetabolites + corticosteroids) was present in 10 cases [13–16,19,21–23,25,27]. Induction therapy with basiliximab was reported in 2 patients. Clinical characteristics, immunosuppressive regimens, and outcomes were reported in Table 1.
Clinical manifestations were heterogenous but often included: cognitive impairment, motor deficits (hemiparesis, ataxia), speech disturbances and visual symptoms.
The median time from transplantation to PML onset was approximately 10 months (1.5–204 months), 57.1% of cases occurred within the first 12 months (early onset), while 42.9% developed after 12 months (late onset); interval was calculated only for patients with available data [14–23,25,26,32]. Three cases did not specify the time from OLTx to PML onset [13,24,27].
Magnetic resonance imaging (MRI) usually led to detection of multifocal white matter lesions. Most cases showed no significant mass effect or contrast enhancement; however, ring enhancement was reported in one case [16]. In 14 cases diagnostic criterion was JCV DNA with polymerase chain reaction (PCR). Neurological manifestations and neuroimaging findings were reported in Table 2. The main therapeutic strategy involved reduction or discontinuation of immunosuppressive therapy; also in selected cases, antiviral agents or immune-modulating approaches were used. Outcomes were generally poor; the mortality rate was very high, 70.6% (n = 12/17) [13,14,16–21,23,25,27]. Some survivors showed persistent neurological impairment, while neurological outcomes were incompletely reported in several cases.
Table 1. Clinical characteristics, immunosuppressive regimens, and outcomes. Due to heterogeneity of reported data, outcomes were reported as after transplantation or after diagnosis.
| Year | Sex / Age | Etiology | IS treatment | Months from LT to PML | Diagnostic basis | PML treatment | Outcome |
| 1994 [13] | F / 53 | HCV | CsA, AZA, steroids | NA | brain biopsy | None | Died 18 months after OLTx |
| 1995 [14] | M / 51 | Cryptogenic | CsA, AZA, methylprednisolone | 1.5 | Brain biopsy | IS withdrawal + cytarabine | Died 8 months after OLTx |
| 2001 [15] | F / 60 | SBC | CsA, AZA, MMF, prednisolone | 10 | JCV PCR (CSF) | IS↓/ withdrawal + cytarabine | Minor improvement; continent of feces |
| 2005 [16] | F / 39 | HCV | Basiliximab, CsA, MMF, steroids → TAC, prednisone | 10 | JCV PCR (CSF) | IS↓ + cytarabine (5 days) | Died 6 weeks after diagnosis |
| 2007 [17] | F / 45 | HCV | TAC, prednisone, CsA | 1.5 | JCV PCR (CSF) | IS↓ | Died 2 months after diagnosis |
| 2009 [32] | F / 66 | HCV | MMF | 113 | JCV PCR (CSF) | IS↓ | Died - time not specified |
| 2011 [18] | F / 71 | HCV | Basiliximab, TAC, MMF | 36 | JCV PCR (CSF) | IS↓ | Died 4 months after diagnosis |
| 2015 [19] | M / 55 | HBV | Prednisolone, MMF, TAC | 9 | JCV PCR (CSF) | IS withdrawal + cytarabine (5 days) | Died 5 weeks after diagnosis |
| 2015 [20] | M / 66 | HCV | TAC, Sirolimus | 48 | JCV PCR (CSF) | IS withdrawal + mefloquine | Died 27 months after diagnosis |
| 2016 [21] | F / 48 | PSC | Prednisolone, MMF, TAC | 144 | JCV PCR (CSF) | IS↓ | Died 26 months after diagnosis |
| 2016 [21] | M / 54 | Alcohol | TAC, steroids | 204 | JCV PCR (CSF) | IS↓ | Alive 36 months after diagnosis |
| 2017 [22] | M / 65 | HCV | TAC, MPA, methylprednisolone | 4 | JCV PCR (CSF) | IS↓ | Alive 4 months after diagnosis |
| 2017 [23] | F / 76 | HCV | TAC, prednisone, MMF | 132 | JCV PCR (CSF) | IS tapering + mirtazapine | Died 2 months after diagnosis |
| 2019 [24] | F / 41 | AIH | TAC, MMF | NA | JCV PCR (CSF) | IS withdrawal; switch to sirolimus | Neurological improvement in 6 months |
| 2019 [25] | M / 59 | HCV | TAC, MMF, steroids | 2.5 | Brain biopsy | IS↓ | Died 3 weeks after diagnosis |
| 2023 [26] | F / 58 | Alcohol | Methylprednisolone, TAC, everolimus | 9 | JCV PCR (CSF) | IS↓ + mirtazapine + mefloquine | Alive 3 years 7 months after diagnosis |
| 2025 [27] | M / 56 | HCV | TAC, MMF, prednisone | NA | JCV PCR (CSF) + brain biopsy | IS withdrawal | Died - time not specified |
Abbreviations: Etiology refers to etiology of liver disease; F – Female, M – Male; AZA – azathioprine; CsA – cyclosporine A; TAC – Tacrolimus; CSF – cerebrospinal fluid; HBV – hepatitis B virus; HCV – hepatitis C virus; IS – immunosuppressant; IS↓ - IS tapering; JCV – JC virus; OLTx – orthotopic liver transplantation; MMF – mycophenolate mofetil; NA – not available; PCR – polymerase chain reaction; PML – progressive multifocal leukoencephalopathy; PSC – primary sclerosing cholangitis; SBC - Secondary Biliary Cirrhosis; MPA – mycophenolic acid; AIH – autoimmune hepatitis
Table 2. Neurological manifestations and neuroimaging findings.
| Year | Sex / Age | Neurological symptoms at presentation | Neuroimaging |
| 1994 [13] | F / 53 | Asymptomatic | Not performed |
| 1995 [14] | M / 51 | Agitation, progressive right hemiparesis, generalized seizure | CT: low attenuation left parietal lobe lesion extending to frontal white matter |
| 2001 [15] | F / 60 | Cognitive impairment, confusion, apathy, incontinence | MRI: widespread asymmetric white matter changes |
| 2005 [16] | F / 39 | Hemiparesis, cognitive decline, coma | MRI: extensive T2/FLAIR hyperintensity in parietal, left frontal/temporal, occipital white matter; ring enhancement |
| 2007 [17] | F / 45 | Weakness, paresthesia, foot drop, peripheral neuropathy | MRI: right frontal white matter lesion extending across corpus callosum |
| 2009 [32] | F / 66 | Left-sided numbness / weakness, fatigue, mild cognitive impairment | MRI: T2/FLAIR hyperintensity in bilateral frontal, right parietal, thalamus, pons, cerebellum |
| 2011 [18] | F / 71 | Vertigo, gait instability, left arm paresis, left hemiparesis | MRI: asymmetric periventricular/subcortical FLAIR hyperintensity |
| 2015 [19] | M / 55 | Weakness, dysarthria | MRI: asymmetric FLAIR hyperintensity in frontoparietal/occipital white matter |
| 2015 [20] | M / 66 | Disorientation, right motor paralysis, apraxia | MRI: enlargement of left frontal lobe lesion |
| 2016 [21] | F / 48 | Progressive monoparesis, limb ataxia, hemianopia | MRI: asymmetric FLAIR hyperintensity right temporoparietal |
| 2016 [21] | M / 54 | Dysarthria, hemiparesis, limb ataxia, diplopia | MRI: asymmetric FLAIR hyperintensity right temporooccipital, cerebellar peduncle |
| 2017 [22] | M / 65 | Psychomotor slowing, homonymous hemianopia, hemiparesis, ataxia | MRI: asymmetric confluent lesions periventricular/subcortical parietooccipital; patchy restricted diffusion |
| 2017 [23] | F / 76 | Spastic paresis of arm, hypertonia, gait disturbance | MRI: bilateral FLAIR hyperintensity in frontal subcortical, thalamus, internal capsule, cerebellum |
| 2019 [24] | F / 41 | Dysarthria, central facial paresis | MRI: high T2/FLAIR signal deep in left hemisphere white matter, splenium |
| 2019 [25] | M / 59 | Cognitive deficits, drowsiness, altered behavior, left hemiparesis | MRI: multiple round/oval lesions with restricted diffusion in bilateral cerebral/cerebellar hemispheres |
| 2023 [26] | F / 58 | Tonic-clonic seizures, acalculia, agraphia | MRI: asymmetric cortex-sparing white matter lesions left frontal/parietal, right parietooccipital |
| 2025 [27] | M / 56 | Bilateral vision loss, intermittent confusion | MRI: increased white matter signal abnormalities in multiple regions |
Abbreviations: F – Female, M – Male; CT – computed tomography; FLAIR - fluid-attenuated inversion recovery; MRI – magnetic resonance imaging.
DISCUSSION
Progressive multifocal leukoencephalopathy after OLTx is rare but associated with significant morbidity and mortality. The condition is rather linked with major immunosuppression, not with single drug. Clinical presentation is often nonspecific, resulting in diagnostic delays.
PML can have different initial symptoms - cognitive and neuropsychiatric alterations (36%–54%), visual disturbances (19%–41%), motor (33%–45%) or sensory impairments (7%–19%), coordination and gait difficulties (13%–35%) or epileptic seizures (5%–14%) [33]. Unlike in multiple sclerosis, the optic nerve and the spinal cord are typically not involved [34]. In our study, clinical presentations were like those reported in the literature. Cognitive impairment was reported in 7 out of 17 patients, visual disturbances in 4, motor in 13, sensory in 2, coordination or gait in 5 and epileptic seizures in 2. One patient did not present neurological symptoms. Asymptomatic patients have already been described in literature, e.g. in natalizumab-treated patients, where diagnosis was based on MRI findings as long as 9 months before clinical diagnosis [35]. This may suggest that PML can be detected before initial symptoms, offering an opportunity for early diagnosis [36].
Patients can be divided into 2 groups: early (<12 months) and late (>12 months) from the onset of PML. Indicating both early and delayed risk patterns, likely reflecting both intensive early immunosuppression and cumulative immunosuppressive burden over time.
Nine cases reported survival time after diagnosis [14,16–21,23,25]. Among them, the median survival from diagnosis was 2 months (0.75–27 months). It highlights the extremely aggressive course of PML after OLTx.
Early diagnosis remains challenging [36,37]. Based on the 2013 consensus published by the Neuroinfectious Disease Section of The American Academy of Neurology, diagnostic classification distinguishes between definite, probable, and possible PML [33]. There are 2 paths to diagnosis, one involves biopsy with histopathological study and JCV DNA detection in material, and the second path, which consists of confirming progressive neurological symptoms, MRI findings, combined with CSF PCR for JC virus [7,38]. The second approach is less invasive and usually preferred [11,36,39,40]. Recent study proposed algorithm based on 2013 diagnostic criteria, which emphasise neuropathological evaluation [5]. Given the rapid progression of the disease, clinicians should maintain a high index of suspicion in transplant recipients presenting new neurological symptoms. In magnetic resonance imaging, the literature describes T2/FLAIR hyperintense lesions that do not respect the border between the white and grey matter. In T1 with or without gadolinium contrast enhancement, or perilesional oedema can be detected. On Diffusion-weighted imaging, a hyperintense signal intensity at the border of an active PML lesion can be found [33,41]. In our study, most cases demonstrated asymmetric white matter lesions with FLAIR hyperintensity and minimal or absent contrast enhancement. Less typical findings, such as mass effect or ring enhancement, were observed in a minority of cases.
Currently, no effective antiviral therapy for JCV exists [1,42]. The development of antiviral strategies against JCV has been slow due to the lack of an animal model of PML, although a variety of new approaches are being tested, including virus-directed T-cell therapies and checkpoint inhibitors [43]. The key to management is restoration of immune function through reduction of immunosuppression. The success of this treatment depends on early diagnosis, limited disease progression and rapid and effective immune repletion [7]. However, this approach carries the risk of graft rejection and immune reconstitution inflammatory syndrome (IRIS), which may paradoxically worsen neurological status [28]. IRIS in natalizumab-treated patients explains why some patients with PML will present symptoms after the treatment of an underlying condition has been initiated: A reconstituted cellular immune response against JCV-infected brain cells can result in overshooting inflammation, structural damage, and new symptoms and may require specific anti-inflammatory therapy to prevent added harm [29,30]. The consensus definition of IRIS in PML has not yet been established.
In comparison to other populations, e.g. HIV-associated PML (mortality 25.9%) or patients treated with monoclonal antibodies for multiple sclerosis (mortality 18-20%), patients after transplantations present a much higher mortality rate (up to 84%) [12,44–46]. One of the reasons is that patients after OLTx may need more careful immunosuppressive therapy reduction due to graft rejection risk.
This review has several limitations. The evidence is based on a small number of published case reports and small case series, without a control group. Therefore, the review cannot estimate the incidence of PML after liver transplantation or determine whether any specific immunosuppressive drug or regimen increases the risk of its development. The included reports differed substantially in the completeness and timing of clinical data, particularly with regard to symptom onset, diagnosis, treatment, follow up, neurological outcome, and survival. In several cases, outcomes were reported from the time of transplantation rather than from PML diagnosis, which limited survival analysis. Quality of the included publications was not assessed. Publication bias is also likely, since severe, unusual, or successfully treated cases are more likely to be published. These limitations prevent firm conclusions regarding prognostic factors, comparative treatment effectiveness, and the optimal strategy for reducing immunosuppression. Standardised multicentre registries are needed to improve the quality and comparability of future data.
CONCLUSION
Progressive multifocal leukoencephalopathy after orthotopic liver transplantation is a rarely reported but severe complication that may develop within the first months or many years after transplantation. Clinical manifestations are heterogeneous and include cognitive, motor, speech, visual, and coordination impairments. Various immunosuppressive regimens were reported in the published cases, while reduction or discontinuation of immunosuppression was the main therapeutic approach after PML diagnosis. Diagnosis was based primarily on brain MRI and the detection of JCV DNA in cerebrospinal fluid, while brain biopsy was used in selected cases. Outcomes were frequently unfavorable, including fatal outcomes and persistent neurological deficits in some survivors. The available evidence does not allow PML to be linked to any specific immunosuppressive regimen or the optimal strategy for reducing immunosuppression to be determined, particularly given the risk of graft rejection.
DISCLOSURE
Conflict of Interest
The authors declare that they have no conflicts of interest.
Funding
This study received no external funding.
Author Contributions
Conceptualization: Kamil Andruszkiewicz, Agata Świątek, Natalia Turzyńska. Methodology: Kamil Andruszkiewicz, Bartosz Machnio. Software: Bartosz Machnio, Mateusz Krysiak. Validation: Wojciech Frączyk, Julia Bąk. Formal analysis: Bogna Błachowska. Investigation: Julia Bąk, Bogna Błachowska. Resources: Wojciech Frączyk, Natalia Jasińska. Data curation: Natalia Turzyńska, Agata Świątek. Writing, original draft: Kamil Andruszkiewicz, Natalia Jasińska. Writing, review and editing: Agnieszka Stankowska, Katarzyna Mania. Visualization: Bogna Błachowska, Agnieszka Stankowska. Supervision: Natalia Turzyńska. Project administration: Kamil Andruszkiewicz.
All authors have read and agreed to the submitted version of the manuscript.
REFERENCES
- Schweitzer F, Laurent S, Cortese I, Fink GR, Silling S, Skripuletz T, et al. Progressive Multifocal Leukoencephalopathy Pathogenesis, Diagnostic Tools, and Potential Biomarkers of Response to Therapy. Neurology. 2023;101:700–13. https://doi.org/10.1212/WNL.0000000000207622
- Tan CS, Koralnik IJ. Progressive multifocal leukoencephalopathy and other disorders caused by JC virus: clinical features and pathogenesis. Lancet Neurol. 2010;9:425–37. https://doi.org/10.1016/S1474-4422(10)70040-5
- Bozic C, Subramanyam M, Richman S, Plavina T, Zhang A, Ticho B. Anti-JC virus (JCV) antibody prevalence in the JCV Epidemiology in MS (JEMS) trial. Eur J Neurol. 2014;21:299–304. https://doi.org/10.1111/ENE.12304
- Weber T, Trebst C, Frye S, Cinque P, Vago L, Sindic CJM, et al. Analysis of the systemic and intrathecal humoral immune response in progressive multifocal leukoencephalopathy. J Infect Dis. 1997;176:250–4. https://doi.org/10.1086/514032
- Sawicka KM, Houpt J, Sangam K, Sivro A, Roy F, Sharma M, et al. Diagnosing progressive multifocal leukoencephalopathy: clinical features, neuroimaging findings, confirmatory testing and proposed diagnostic algorithm. Pract Neurol. 2026;pn-2025-004648. https://doi.org/10.1136/PN-2025-004648
- Joly M, Conte C, Cazanave C, Le Moing V, Tattevin P, Delobel P, et al. Progressive multifocal leukoencephalopathy: epidemiology and spectrum of predisposing conditions. Brain. 2023;146:349–58. https://doi.org/10.1093/BRAIN/AWAC237
- Cortese I, Reich DS, Nath A. Progressive multifocal leukoencephalopathy and the spectrum of JC virus-related disease. Nat Rev Neurol. 2020;17:37. https://doi.org/10.1038/S41582-020-00427-Y
- Sipilä JOT, Soilu-Hänninen M, Rautava P, Kytö V. Progressive multifocal leukoencephalopathy in Finland: a cross-sectional registry study. J Neurol. 2019;266:515–21. https://doi.org/10.1007/S00415-018-09167-Y
- Wang Z, Sheng K, Wang Y, Luo J, Guo M. Viral infections in solid organ transplant recipients: immunological principles and intervention strategies. Am J Transl Res. 2026;18:13. https://doi.org/10.62347/ZSRU1567
- Blankenbach K, Schwab N, Hofner B, Adams O, Keller-Stanislawski B, Warnke C. Natalizumab-associated progressive multifocal leukoencephalopathy in Germany. Neurology. 2019;92:e2232–9. https://doi.org/10.1212/WNL.0000000000007451
- Wijburg MT, Warnke C, Barkhof F, Uitdehaag BMJ, Killestein J, Wattjes MP. Performance of PML diagnostic criteria in natalizumab-associated PML: data from the Dutch-Belgian cohort. J Neurol Neurosurg Psychiatry. 2019;90:44–6. https://doi.org/10.1136/JNNP-2018-318261
- Mateen FJ, Muralidharan R, Carone M, Van De Beek D, Harrison DM, Aksamit AJ, et al. Progressive Multifocal Leukoencephalopathy in Transplant Recipients. Ann Neurol. 2011;70:305. https://doi.org/10.1002/ANA.22408
- Worthmann F, Türker T, Müller AR, Patt S, Stoltenburg-Didinger G. Progressive multifocal leukoencephalopathy after orthotopic liver transplantation. Transplantation. 1994;57:1268–71. https://doi.org/10.1097/00007890-199404270-00023
- Bronster DJ, Lidov MW, Wolfe D, Schwartz ME, Miller CM. Progressive multifocal leukoencephalopathy after orthotopic liver transplantation. Liver Transpl Surg. 1995;1:371–2. https://doi.org/10.1002/LT.500010606
- Boulton-Jones JR, Fraser-Moodie C, Ryder SD. Long term survival from progressive multifocal leucoencephalopathy after liver transplantation. J Hepatol. 2001;35:828–9. https://doi.org/10.1016/S0168-8278(01)00202-1
- Lima MA, Hanto DW, Curry MP, Wong MT, Dang X, Koralnik IJ. Atypical radiological presentation of progressive multifocal leukoencephalopathy following liver transplantation. J Neurovirol. 2005;11:46–50. https://doi.org/10.1080/13550280590900742
- Mohanty SR, Testa G, LaBrecque DR, Mitros FA. Progressive Multifocal Leukoencephalopathy With Peripheral Demyelinating Neuropathy in a Liver Transplant Patient. Gastroenterol Hepatol (N Y). 2007;3:70. https://pmc.ncbi.nlm.nih.gov/articles/PMC3096122/
- Verhelst X, Vanhooren G, Vanopdenbosch L, Casselman J, Laleman W, Pirenne J, et al. Progressive multifocal leukoencephalopathy in liver transplant recipients: a case report and review of the literature. Transpl Int. 2011;24:e30–4. https://doi.org/10.1111/J.1432-2277.2010.01190.X
- Ozdemir F, Ince V, Baskiran A, Ozdemir Z, Bayindir Y, Otlu B, et al. Progressive Multifocal Leukoencephalopathy after Three Consecutive Liver Transplantations. Int J Organ Transplant Med. 2015;6:126. https://pmc.ncbi.nlm.nih.gov/articles/PMC4545307
- Yoshida T, Kawamoto M, Togo M, Kohara N, Ito T, Nakamichi K, et al. Progressive multifocal leukoencephalopathy developing after liver transplantation showing marked neurological symptom improvement and arrest of further deterioration of imaging findings: A case report. J Neurol Sci. 2015;359:1–3. https://doi.org/10.1016/j.jns.2015.10.028
- Dumortier J, Guillaud O, Bosch A, Coppéré B, Petiot P, Roggerone S, et al. Progressive multifocal leukoencephalopathy after liver transplantation can have favorable or unfavorable outcome. Transpl Infect Dis. 2016;18:606–10. https://doi.org/10.1111/TID.12554
- Avsenik J, Horvat Ledinek A, Šurlan Popovič K. Progressive multifocal leukoencephalopathy - immune reconstitution inflammatory syndrome (PML-IRIS) in liver transplant recipient. Mult Scler Relat Disord. 2017;17:135–7. https://doi.org/10.1016/j.msard.2017.07.018
- Moreno-Estébanez A, Almeida Velasco J, Pérez-Concha T, González-Pinto T, Gabilondo I. Progressive multifocal leukoencephalopathy 11 years after liver transplantation: a case report. J Neurovirol. 2017;23:929–31. https://doi.org/10.1007/S13365-017-0578-0
- Ahmadinejad Z, Talebi F, Yazdi NA, Ghiasvand F. A 41-year-old female with progressive multifocal leukoencephalopathy after liver transplant. J Neurovirol. 2019;25:605–7. https://doi.org/10.1007/S13365-019-00742-1
- Rastogi A, Gulati N, Bihari C, Chaudhary A, Bansal K, Sasturkar S, et al. JC virus-related progressive multifocal leukoencephalopathy after living-donor liver transplant: A rare case. Exp Clin Transplant. 2019;17:414–7. https://doi.org/10.6002/ECT.2016.0242
- Egashira S, Kubota A, Kakumoto T, Kawasaki R, Kotani R, Sakuishi K, et al. Long-term survival from progressive multifocal leukoencephalopathy in living-donor liver transplant recipient with preformed donor-specific antibody. J Neurovirol. 2023;29:519. https://doi.org/10.1007/S13365-023-01171-X
- Khan A, Grzybowski K, Paramashivaiah S, Javaid A, Zafar S, Lagarde M, et al. Confronting the Complexity of PML: Difficult Management Decisions. Am J Gastroenterol. 2025;120:S1199. https://doi.org/10.14309/01.AJG.0001149948.34556.5B
- Ishii K, Yamamoto F, Homma S, Okada Y, Nakamichi K, Saijo M, et al. Probable progressive multifocal leukoencephalopathy-immune reconstitution inflammatory syndrome with immunosuppressant dose reduction following lung transplantation: a case report and literature review. BMC Neurol. 2019;19. https://doi.org/10.1186/S12883-019-1493-1
- Tan IL, McArthur JC, Clifford DB, Major EO, Nath A. Immune reconstitution inflammatory syndrome in natalizumab-associated PML. Neurology. 2011;77:1061–7. https://doi.org/10.1212/WNL.0B013E31822E55E7
- Wattjes MP, Wijburg MT, van Eijk J, Frequin S, Uitdehaag BMJ, Barkhof F, et al. Inflammatory natalizumab-associated PML: baseline characteristics, lesion evolution and relation with PML-IRIS. J Neurol Neurosurg Psychiatry. 2018;89:535–41. https://doi.org/10.1136/JNNP-2017-316886
- Page MJ, McKenzie JE, Bossuyt PM, Boutron I, Hoffmann TC, Mulrow CD, et al. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ. 2021;372. https://doi.org/10.1136/BMJ.N71
- Yehia B, Davison A, Sisson S. Transplant Troubles. Am J Med. 2009;122:629–31. https://doi.org/10.1016/j.amjmed.2009.04.001
- Berger JR, Aksamit AJ, Clifford DB, Davis L, Koralnik IJ, Sejvar JJ, et al. PML diagnostic criteria. Neurology. 2013;80:1430–8. https://doi.org/10.1212/WNL.0B013E31828C2FA1
- Moussaoui N El, Lambert N, Moussaoui M El, Bianchi E, Léonard P, Moïse M, et al. Spinal cord involvement in progressive multifocal leukoencephalopathy and immune reconstitution inflammatory syndrome. J Neurovirol. 2024;30:208–13. https://doi.org/10.1007/S13365-024-01213-Y
- Blair NF, Brew BJ, Halpern JP. Natalizumab-associated PML identified in the presymptomatic phase using MRI surveillance. Neurology. 2012;78:507–8. https://doi.org/10.1212/WNL.0B013E318246D6D8
- Baldassari LE, Wattjes MP, Cortese ICM, Gass A, Metz I, Yousry T, et al. The neuroradiology of progressive multifocal leukoencephalopathy: a clinical trial perspective. Brain. 2022;145:426–40. https://doi.org/10.1093/BRAIN/AWAB419
- Miskin DP, Ngo LH, Koralnik IJ. Diagnostic delay in progressive multifocal leukoencephalopathy. Ann Clin Transl Neurol. 2016;3:386–91. https://doi.org/10.1002/ACN3.301
- Nakamichi K, Kawamoto M, Ishii J, Saijo M. Improving detection of JC virus by ultrafiltration of cerebrospinal fluid before polymerase chain reaction for the diagnosis of progressive multifocal leukoencephalopathy. BMC Neurol. 2019;19. https://doi.org/10.1186/S12883-019-1476-2
- Wattjes MP, Vennegoor A, Steenwijk MD, De Vos M, Killestein J, Van Oosten BW, et al. MRI pattern in asymptomatic natalizumab-associated PML. J Neurol Neurosurg Psychiatry. 2015;86:793–8. https://doi.org/10.1136/JNNP-2014-308630
- Wijburg MT, Kleerekooper I, Lissenberg-Witte BI, De Vos M, Warnke C, Uitdehaag BMJ, et al. Association of Progressive Multifocal Leukoencephalopathy Lesion Volume With JC Virus Polymerase Chain Reaction Results in Cerebrospinal Fluid of Natalizumab-Treated Patients With Multiple Sclerosis. JAMA Neurol. 2018;75:827–33. https://doi.org/10.1001/JAMANEUROL.2018.0094
- Sahraian MA, Radue EW, Eshaghi A, Besliu S, Minagar A. Progressive multifocal leukoencephalopathy: a review of the neuroimaging features and differential diagnosis. Eur J Neurol. 2012;19:1060–9. https://doi.org/10.1111/J.1468-1331.2011.03597.X
- Gheuens S, Pierone G, Peeters P, Koralnik IJ. Progressive multifocal leukoencephalopathy in individuals with minimal or occult immunosuppression. J Neurol Neurosurg Psychiatry. 2010;81:247–54. https://doi.org/10.1136/JNNP.2009.187666
- Cortese I, Beck ES, Al-Louzi O, Ohayon J, Andrada F, Osuorah I, et al. BK virus-specific T cells for immunotherapy of progressive multifocal leukoencephalopathy: an open-label, single-cohort pilot study. Lancet Neurol. 2021;20:639–52. https://doi.org/10.1016/S1474-4422(21)00174-5
- Kappos L, Bates D, Edan G, Eraksoy M, Garcia-Merino A, Grigoriadis N, et al. Natalizumab treatment for multiple sclerosis: updated recommendations for patient selection and monitoring. Lancet Neurol. 2011;10:745–58. https://doi.org/10.1016/S1474-4422(11)70149-1
- Major EO, Yousry TA, Clifford DB. Pathogenesis of progressive multifocal leukoencephalopathy and risks associated with treatments for multiple sclerosis: a decade of lessons learned. Lancet Neurol. 2018;17:467–80. https://doi.org/10.1016/S1474-4422(18)30040-1
- Kim J, Kim C, Lee JA, Lee SJ, Lee KH, Kim JH, et al. Long-term prognosis and overall mortality in patients with progressive multifocal leukoencephalopathy. Sci Rep. 2023;13. https://doi.org/10.1038/S41598-023-41147-9